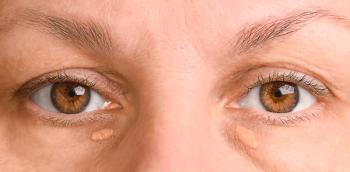
Yellow eyelid Xanthelasma signals hidden high cholesterol and cardiovascular disease risk, tripling heart attack and stroke odds; Negin Yavari, M.D., and her team urge screening.
Heart disease became the leading cause of death among Hispanic adults in the U.S. in 2022, and a new American Heart Association statement says risk varies by heritage, with gaps in coverage, language and food access adding to the burden.
Cardiovascular disease (CVD) became the leading cause of death in Hispanic adults in the U.S. in 2022,
According to a scientific statement from the American Heart Association (AHA) published Sept. 15, 2026, in
For years, researchers pointed to a “Hispanic paradox,” or lower death rates from heart disease despite more risk factors. The scientific statement noted that idea is too simple, since it isn’t true for every heritage group, sex or type of heart disease. Growing gaps in blood pressure control, obesity and diabetes also put that advantage at risk.
Risk varies by heritage, and disease shows up sooner.
Risk factors are common, and they vary by heritage. According to the statement, about 46% of Hispanic adults have obesity, with the highest rates among Puerto Rican and Dominican adults. Type 2 diabetes affects 15.5%, nearly double the rate among non-Hispanic white adults, and it is most common among Mexican and Puerto Rican adults. It also more often goes undiagnosed.
It was also found that roughly 44% have high blood pressure, similar to non-Hispanic white adults, and it is most common among Puerto Rican, Cuban and Dominican adults. Cuban adults have the highest rates of high LDL cholesterol, and Dominican adults have the highest triglyceride levels. Among women in HCHS/SOL, 71% had at least one heart disease risk factor, with the highest burden among Puerto Rican women and the lowest among South American women.
Control is a challenge, too. Hispanic adults are less likely than non-Hispanic white adults to know they have high blood pressure, get treated or bring it under control. Among HCHS/SOL participants with diabetes, 43% met blood sugar targets, 49% met blood pressure targets and 37% met LDL cholesterol targets. Just 8.4% met all three.
Disease also shows up sooner. Hispanic adults are diagnosed with heart failure eight to nine years earlier than non-Hispanic white adults. The average age at first stroke is about 67 among Hispanic adults, compared with 73 to 75 among white adults. Hispanic adults also had lower average scores than non-Hispanic white adults on the AHA's Life's Essential 8 measure of heart health. Outcomes also differ by birthplace: U.S.-born Hispanic adults have shorter life expectancy and higher death rates than those born abroad.
Gaps in coverage and care
The statement also points to gaps in coverage and care. About 20% of Hispanic adults were uninsured in 2023, compared with 6.4% of white adults.
Hispanic adults are also less likely to receive cholesterol-lowering drugs or advanced heart failure therapies. Language and food access are barriers, as well. To assist these areas, the statement points to community health workers, who work in trusted places such as churches and community centers, and to food programs such as medically tailored groceries and produce prescriptions.
“Raising awareness about these disparities is important, but awareness without access is not enough,” Contreras said in an
Limits and what comes next
The statement draws on large national datasets and long-running studies, and it looks at differences by heritage group instead of treating Hispanic adults as one population. It also covers children, women and social factors, not just disease rates. However, this statement has limits. For instance, it is a review, not new research. Some figures rely on HCHS/SOL data collected as early as 2008. Many datasets still lump Hispanic adults together, which hides differences between groups, as well.
Hispanic people remain underrepresented in clinical trials and genetic studies, and common risk calculators have limited testing in Hispanic populations. Many of the links described, such as those tied to acculturation, come from observational research, which shows associations and cannot prove cause.
The authors say in the statement the next steps start with better data and broader inclusion.
“Future research should prioritize the inclusion of diverse Hispanic heritage groups, disaggregated data collection, and integration of social determinants to refine risk prediction, treatment strategies, and policy interventions,” Contreras and her team wrote.
Her team also calls for culturally tailored care, more bilingual clinicians and safeguards against bias in artificial intelligence tools. These efforts are also essential to achieving the AHA’s